A treatment can improve liver tissue before researchers know whether it prevents liver failure or helps people feel better. That distinction is central to ESSENCE, a phase 3 trial of injectable semaglutide in people with metabolic dysfunction-associated steatohepatitis, or MASH, and moderate or advanced liver scarring. Its planned 72-week analysis found better biopsy outcomes with semaglutide than placebo, but did not establish the longer-term effects on death, transplantation, or other serious liver events.
The FDA has granted Wegovy injection accelerated approval for adults with MASH and moderate-to-advanced fibrosis. That is an existing indication, not merely a research proposal. The practical question is how to understand the evidence supporting it without turning a tissue result into an unsupported promise about symptoms, survival, or a particular care service. This analysis uses the indexed primary research abstracts and available official FDA material, rather than a review of complete trial protocols, supplements, and full texts.
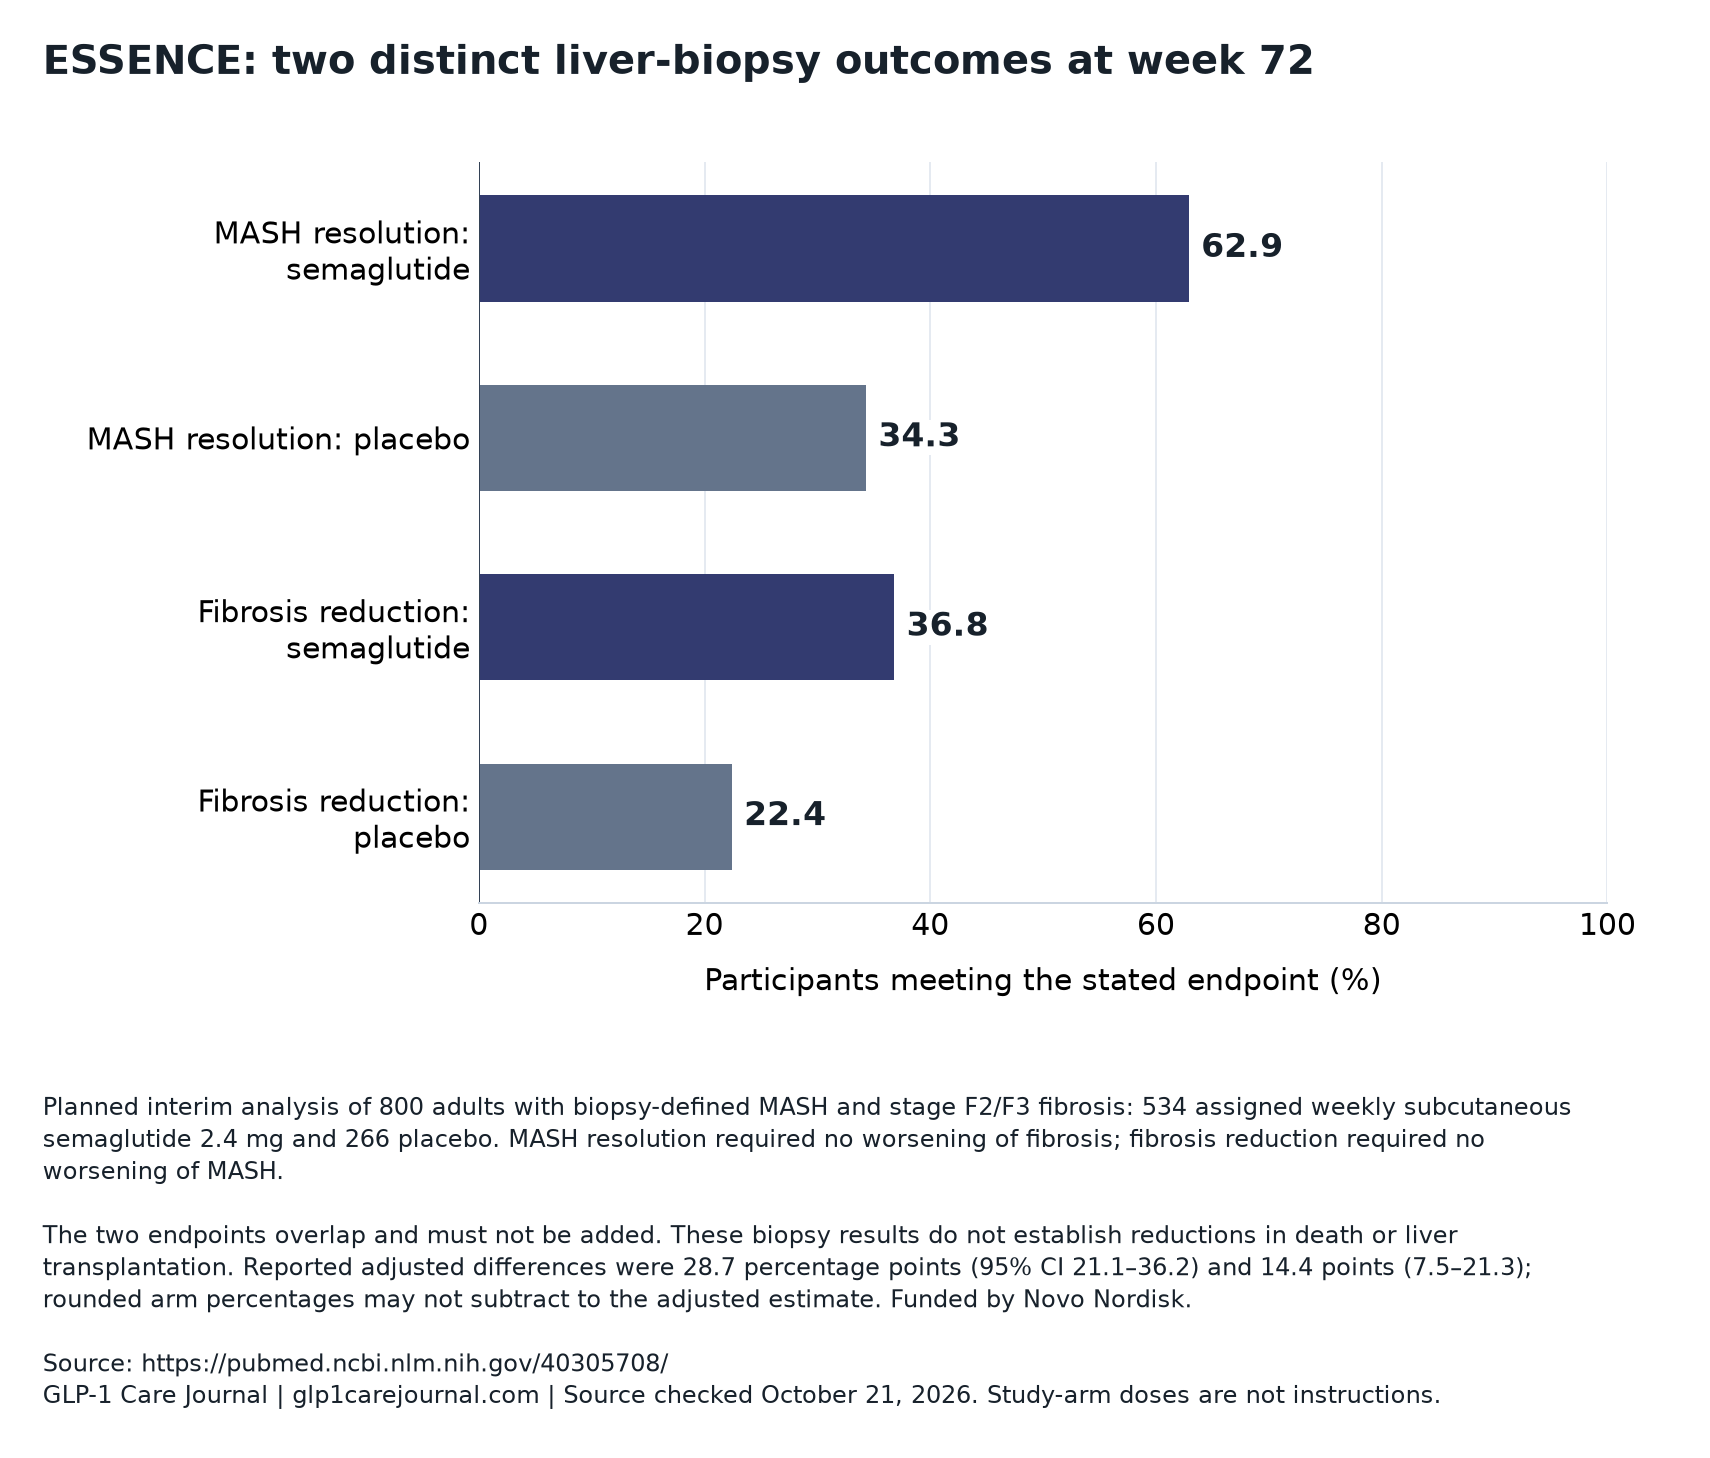
ESSENCE: two distinct liver-biopsy outcomes at week 72
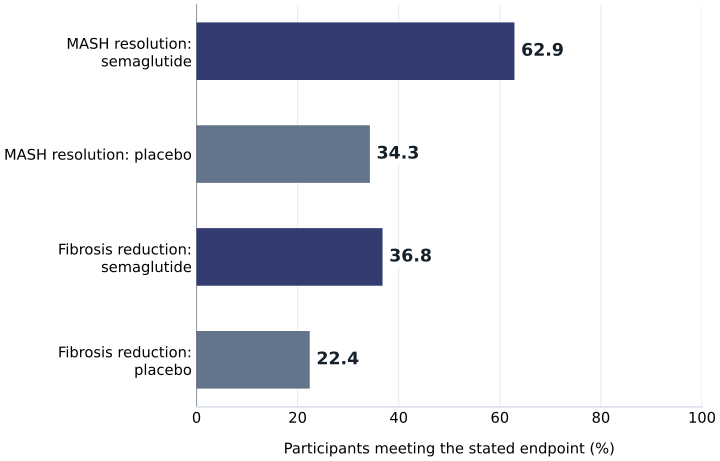
Planned interim analysis of 800 adults with biopsy-defined MASH and stage F2/F3 fibrosis: 534 assigned weekly subcutaneous semaglutide 2.4 mg and 266 placebo. MASH resolution required no worsening of fibrosis; fibrosis reduction required no worsening of MASH.
The two endpoints overlap and must not be added. These biopsy results do not establish reductions in death or liver transplantation. Reported adjusted differences were 28.7 percentage points (95% CI 21.1–36.2) and 14.4 points (7.5–21.3); rounded arm percentages may not subtract to the adjusted estimate. Funded by Novo Nordisk.
Source 1Download the source-labeled chart (PNG) · Download the data (CSV)
| Study group | Reported value |
|---|---|
| MASH resolution: semaglutide | 62.9 |
| MASH resolution: placebo | 34.3 |
| Fibrosis reduction: semaglutide | 36.8 |
| Fibrosis reduction: placebo | 22.4 |
Sections in this article
The liver disease ESSENCE actually studied
MASH involves fat buildup accompanied by liver inflammation and injury, with scarring developing in some people. Fibrosis means scar tissue; it is not interchangeable with inflammation. ESSENCE required biopsy-defined disease and fibrosis stage 2 or 3, commonly described as moderate or advanced fibrosis. These were noncirrhotic disease stages, so the findings should not be treated as a trial result for established cirrhosis.
The entry criteria matter because a broad label such as fatty liver covers people with very different starting risks. A person with an incidental imaging finding is not automatically comparable to someone whose tissue sample established MASH with F2 or F3 scarring. The study's benefit estimates belong first to its selected population, not to everyone with an elevated liver enzyme or excess liver fat.
Symptoms also offer an incomplete guide to this disease. FDA describes MASH as potentially progressing to cirrhosis, worsening liver function, cancer, transplantation, or death, while many people have no symptoms until severe damage develops. That helps explain why researchers measured tissue changes even though a biopsy response is not itself something a patient necessarily feels.
Source 1 Source 2How the 72-week comparison was built
ESSENCE is a multicenter, randomized, double-blind, placebo-controlled trial funded by Novo Nordisk. Investigators assigned 1,197 participants in a 2:1 ratio to once-weekly subcutaneous semaglutide, meaning injection under the skin, at 2.4 mg or placebo for a planned 240 weeks. That dose identifies the research arm; it is not an individualized treatment instruction.
The published interim report concerns the first 800 participants at week 72: 534 assigned semaglutide and 266 assigned placebo. This was a planned analysis, not the completed follow-up of all 1,197 participants. Random assignment supports a causal comparison between the assigned treatments, while blinding reduces the opportunity for knowledge of treatment to influence trial conduct or assessment.
According to FDA's account, both groups also received lifestyle interventions, including dietary modification and increased physical activity, and participants were on stable doses of relevant background medications. Thus, the comparison was not medication versus an absence of care. The abstract does not provide enough detail to reconstruct adherence, missing-biopsy handling, or every feature of outcome assessment.
Source 1 Source 2Reading the two primary biopsy endpoints
The first primary endpoint asked whether steatohepatitis resolved without fibrosis getting worse. It occurred in 62.9% of the semaglutide group and 34.3% of the placebo group. The reported estimated difference was 28.7 percentage points, with a 95% confidence interval of 21.1 to 36.2. Although the displayed percentages subtract to 28.6, the reported estimate should be retained rather than replaced with arithmetic on rounded figures.
The second primary endpoint asked whether fibrosis decreased without steatohepatitis worsening. Rates were 36.8% and 22.4%, respectively, with an estimated difference of 14.4 percentage points and a 95% confidence interval of 7.5 to 21.3. Both intervals exclude zero, supporting a treatment difference, while their widths show uncertainty about its precise magnitude.
These are absolute percentage-point differences, not relative reductions in liver failure risk. Roughly speaking, the first estimate corresponds to about 29 additional biopsy responders per 100 comparable participants at this assessment. It does not mean 29 fewer transplantations, nor does resolution without worsening scarring require that scarring actually improved.
| Endpoint | Semaglutide versus placebo | Reported difference, 95% CI |
|---|---|---|
| Steatohepatitis resolution without worsening fibrosis | 62.9% versus 34.3% | 28.7 percentage points; 21.1 to 36.2 |
| Fibrosis reduction without worsening steatohepatitis | 36.8% versus 22.4% | 14.4 percentage points; 7.5 to 21.3 |
| Both steatohepatitis resolution and fibrosis reduction | 32.7% versus 16.1% | 16.5 percentage points; 10.2 to 22.8 |
Why the response categories cannot be added
A prespecified secondary outcome required both steatohepatitis resolution and fibrosis reduction. This occurred in 32.7% with semaglutide and 16.1% with placebo. The reported estimated difference was 16.5 percentage points, with a 95% confidence interval of 10.2 to 22.8. Again, the estimated difference need not equal subtraction of the rounded displayed rates.
The joint endpoint helps distinguish two patterns that the primary endpoints separately allow. Someone can have inflammation resolve while scarring remains unchanged, or have scarring improve without complete resolution of steatohepatitis. Requiring both improvements is a stricter question than requiring either improvement with no worsening of the other feature.
These categories overlap. Adding 62.9% and 36.8% would count some people twice and would not produce a valid overall response rate. The joint result also prevents a loose claim that nearly two-thirds experienced both forms of improvement. The report supports nearly two-thirds meeting the resolution-without-worsening endpoint, not nearly two-thirds reversing both inflammation and fibrosis.
Source 1Weight change was clear; pain relief was not
Mean body weight changed by −10.5% with semaglutide and −2.0% with placebo. The estimated between-group difference was −8.5 percentage points, with a 95% confidence interval of −9.6 to −7.4. These are group averages rather than predictions for every participant. Weight change and biopsy change were different outcomes, even though both favored semaglutide.
The abstract does not establish how much of the liver benefit was caused by weight loss versus other pathways. FDA describes weight loss and other incompletely understood mechanisms as possible contributors. Demonstrating two treatment-associated changes is not the same as demonstrating the causal pathway connecting them.
Mean changes in bodily pain scores did not differ significantly. That finding does not establish that all symptoms were unchanged, or that no individual felt better; it means this comparison did not demonstrate a pain-score advantage. For everyday records, keeping weight, symptoms, and liver assessments in distinct fields—as in a usable medication record—avoids treating one favorable measurement as proof that every dimension improved.
Source 1 Source 2Accelerated approval preserves a second scientific question
FDA approved Wegovy injection for adults with MASH and moderate-to-advanced fibrosis through its accelerated approval pathway. This pathway permits approval for a serious condition based on a surrogate endpoint, with additional evidence required to confirm effects on clinically meaningful outcomes. Here, the surrogate is histology: the appearance of liver tissue under a microscope.
That decision recognizes the importance of the biopsy findings without making them identical to survival or avoidance of transplantation. FDA states that ESSENCE will continue to 240 weeks to investigate whether the earlier inflammation and scarring improvements translate into fewer deaths, liver transplants, and other liver-related events.
The accurate conclusion is therefore specific: this 72-week analysis establishes improved histologic outcomes, not the trial's eventual clinical-event benefit. It is neither accurate to call the indication still investigational nor to describe longer-term liver-event prevention as already demonstrated by this report. A later clinical result would answer an additional question rather than merely restating the biopsy result.
Source 2 Source 1Safety needs its own outcome record
Gastrointestinal adverse events were more common in the semaglutide arm of ESSENCE. The indexed abstract does not provide their counts, severity distribution, or treatment-discontinuation rates. That limits a numerical benefit–harm comparison within this analysis; it does not justify describing the intervention simply as safe or assuming every event was mild.
FDA's approval announcement lists nausea, diarrhea, vomiting, constipation, abdominal pain, and other adverse effects among commonly reported effects of Wegovy. It also identifies contraindications involving personal or family history of medullary thyroid cancer, multiple endocrine neoplasia type 2, and known sensitivity to the drug or its ingredients. The announcement is not a substitute for complete current prescribing information.
A practical editorial interpretation is that tolerability deserves documentation alongside effectiveness. A biopsy result, symptom burden, and an interruption in treatment describe different parts of care. One-page notes after a care visit can help preserve what was reported and what follow-up was arranged without requiring a patient to decide whether a symptom was definitely drug-caused.
Source 1 Source 2SELECT and FLOW answer different endpoint questions
Semaglutide has also been tested against clinical events, but those trials cannot supply missing MASH outcomes. SELECT enrolled 17,604 people aged at least 45 with established cardiovascular disease, BMI of at least 27, and no diabetes. With the same weekly injected 2.4-mg research dose, its cardiovascular composite occurred in 6.5% versus 8.0% over a mean 39.8 months of follow-up.
SELECT's hazard ratio was 0.80, with a 95% confidence interval of 0.72 to 0.90. This describes a 20% lower hazard for the composite over follow-up, not a 20-percentage-point reduction. Permanent discontinuation because of adverse events occurred in 16.6% versus 8.2%. Neither the benefit nor the discontinuation rate should be substituted for ESSENCE's own estimates.
FLOW studied 3,533 people with type 2 diabetes and chronic kidney disease using weekly injected semaglutide 1.0 mg. Its primary composite had 331 versus 410 first events: hazard ratio 0.76, 95% confidence interval 0.66 to 0.88, over median follow-up of 3.4 years. The trial stopped early following a prespecified interim analysis. Serious adverse events occurred in 49.6% versus 53.8%. These findings demonstrate why population, dose, endpoint, and follow-up must travel together.
| Trial and population | Intervention and comparator | Primary endpoint focus |
|---|---|---|
| ESSENCE: biopsy-defined MASH with F2/F3 fibrosis | Weekly subcutaneous semaglutide 2.4 mg versus placebo | Two histologic endpoints at the planned 72-week analysis |
| SELECT: established cardiovascular disease, overweight or obesity, no diabetes | Weekly subcutaneous semaglutide 2.4 mg versus placebo | Cardiovascular death, nonfatal heart attack, or nonfatal stroke |
| FLOW: type 2 diabetes and chronic kidney disease | Weekly subcutaneous semaglutide 1.0 mg versus placebo | Kidney failure, at least 50% eGFR decline, or kidney-related or cardiovascular death |
Neither oral results nor compounded products inherit ESSENCE
A shared GLP-1 label does not make different molecules, routes, or formulations interchangeable evidence. ATTAIN-1 studied daily oral orforglipron in 3,127 adults with obesity without diabetes, with weight change as its primary endpoint. Its 36-mg group averaged an 11.2% weight reduction at 72 weeks versus 2.1% with placebo. Those figures are not a MASH biopsy comparison.
The ATTAIN-1 evidence analysis examines that separate oral-drug question. Similar-looking weight averages across trials do not establish equal liver effects: enrollment criteria, treatments, and primary endpoints differ. ESSENCE's results likewise do not establish MASH effectiveness for oral semaglutide or another formulation not evaluated in this comparison.
Compounded products introduce another distinction. FDA states that they are not FDA approved and do not undergo its premarket review for safety, effectiveness, and quality. It has received reports involving dosing errors with compounded injectable semaglutide, including some requiring hospitalization. Such reports do not provide a comparative event rate, but they reinforce why an approved-product trial cannot validate a compounded product or its supplier.
Source 1 Source 5 Source 6What the evidence means for follow-up and the care budget
Editorial interpretation: a care budget should distinguish paying for access from obtaining evidence-based disease follow-up. ESSENCE did not measure subscription value, insurance coverage, service quality, or household costs. A favorable trial result therefore cannot tell readers which service is affordable or whether a contract includes the records and coordination relevant to their care.
The useful documentary questions are concrete: what product is identified, what visits or tests are included, who receives outside results, and what happens to records when care changes? The everyday provider comparison guide and continuity-of-care guide offer context for organizing those questions. They do not convert a commercial offering into the ESSENCE treatment setting.
For a service under consideration, the Ro review or Found review can be used to check documentary terms, not to infer that either offers the studied product, MASH-specific care, or trial-like outcomes. The central research lesson is to keep three records distinct: what the treatment was, what the patient experienced, and what objective follow-up actually established.
Source 1 Source 2 Source 6Questions about the evidence
Does MASH resolution mean the liver has no remaining scarring?
No. The first primary endpoint required steatohepatitis resolution without worsening fibrosis, so unchanged scarring could still qualify. Fibrosis reduction was evaluated separately. The joint endpoint, met by 32.7% with semaglutide and 16.1% with placebo, required both resolution and fibrosis improvement. Even that endpoint should not be translated into complete removal of all scar tissue.
Source 1Why did so many placebo participants also improve?
The placebo group was not untreated: FDA describes lifestyle interventions and stable background medications in both groups. The available abstract does not determine how much each factor contributed to placebo-group responses. The randomized between-group difference is therefore more informative about the assigned drug's added effect than the semaglutide response percentage considered alone.
Source 1 Source 2Does the 72-week report show fewer liver transplants or deaths?
No. Its primary outcomes were biopsy-based. FDA identifies the planned 240-week continuation as the part intended to determine whether tissue improvements translate into fewer deaths, transplants, and other liver-related events. This is a statement about what the 72-week analysis establishes, not a claim about every result that may emerge from later research.
Source 1 Source 2Can SELECT or FLOW prove that every major complication improves in MASH?
No. Those trials studied different populations and composite endpoints. A composite groups several event types into one analysis; an overall reduction does not establish that every component improved independently. SELECT's cardiovascular result and FLOW's kidney-focused result are important, but neither replaces a direct analysis of liver events in the ESSENCE population.
Source 3 Source 4 Source 1What is most useful to preserve when care moves between services?
As an editorial interpretation, preserve the actual medication identity and route, disease assessments, reported adverse effects, and dated follow-up findings rather than only a summary saying treatment worked. A weight change, a pain report, and a biopsy response answer different questions. ESSENCE provides no evidence that transferring care to a particular provider preserves its outcomes.
Source 1 Source 6Editorial assessment
ESSENCE provides convincing randomized evidence that weekly injected semaglutide improved two prespecified biopsy outcomes in people with MASH and F2 or F3 fibrosis at 72 weeks. The absolute differences were substantial, and the joint endpoint supports improvement in both inflammation and scarring for a subset of participants. Weight reduction was also greater, but pain-score improvement was not demonstrated and gastrointestinal adverse events were more common. The existing accelerated approval recognizes these tissue findings while retaining the need to confirm meaningful clinical benefit. For care decisions and recordkeeping, the strongest interpretation is precise rather than expansive: document the studied treatment, distinguish tissue response from lived experience, and do not substitute results from another population, formulation, or service.
Research access and limitations
This analysis relies on indexed primary report abstracts and available official FDA material. It does not independently assess complete protocols, biopsy adjudication procedures, missing-data methods, supplements, or current prescribing information. The ESSENCE abstract does not supply detailed adverse-event counts or establish the longer-term clinical outcomes discussed here.
Source notes
Scientific sources checked October 21, 2026. Earlier research and provider sources retain their dated histories below. Provider pages document advertised terms. Study summaries identify the scope of our review.
- Phase 3 Trial of Semaglutide in Metabolic Dysfunction-Associated Steatohepatitis.Indexed original research abstract · Checked 2026-10-21
- FDA approves treatment for serious liver disease known as MASHOfficial FDA page read through web tool; historical approval announcement, not complete current labeling · Checked 2026-10-21
- Semaglutide and Cardiovascular Outcomes in Obesity without Diabetes.Primary research or official information · Checked 2026-10-21
- Effects of Semaglutide on Chronic Kidney Disease in Patients with Type 2 Diabetes.Primary research or official information · Checked 2026-10-21
- Orforglipron, an Oral Small-Molecule GLP-1 Receptor Agonist for Obesity Treatment.Indexed original research abstract · Checked 2026-10-21
- FDA — unapproved GLP-1 drug concernsSafety information · Checked 2026-10-21